Peptide Dosage: Label vs Blank Panel Map
Key takeaways
- Verdict: “Peptide dosage” is not one chart. Label dose, clinic plan, and research blank panel are three different doors.
- How it works in one line: Labeled peptide drugs publish studied amounts. Research-shelf vials often do not. Reconstitution strength changes how people talk about a “dose.”
- Your next step: learn units literacy and pick a door. No free-site protocol table here.
Verdict up front: a search for peptide dosage deserves a clean answer. Peptides are short chains of amino acids. Amino acids are the building blocks your body already uses to make proteins. Some peptide drugs are FDA-approved medicines with labels and studied amounts. Some research vials still live mostly in animal papers and thin human pilots. Mixing those lanes is how people get a fake “one dosage chart” online.
This page is a dose map. It is not a free protocol. It will not publish milligram schedules for research vials. It will not tell you a catalog vial treats disease. It will not tell you to skip a clinician.
Keep reading if you typed peptide dosage, peptide dosing, mcg vs mg, IU, U-100 units, reconstitution math, research peptides, or peptide therapy and want honesty first. Skip if you want a public milligram table. Skip if you want a claim that a catalog vial is proven therapy. Skip if you want a reason to ignore a doctor. Those asks belong in Pro. Or a real clinic visit.
Day-one basics live on Start Here and what are peptides. Nearby maps: how to reconstitute peptides, bacteriostatic water, peptide calculator, peptide side effects, peptide therapy, are peptides safe, peptide injections, BPC-157, TB-500, semaglutide, and HGH peptides.
This page is teaching only, not medical advice. Research-shelf curiosity is not an FDA-approved treatment claim. Real drug labels belong to clinics. This map will not tell you to skip a doctor.
What people mean when they ask about peptide dosage
Start with the plain search. Most people are not asking about every molecule that ends in -tide. They are asking how much of the vial or pen in a forum post.
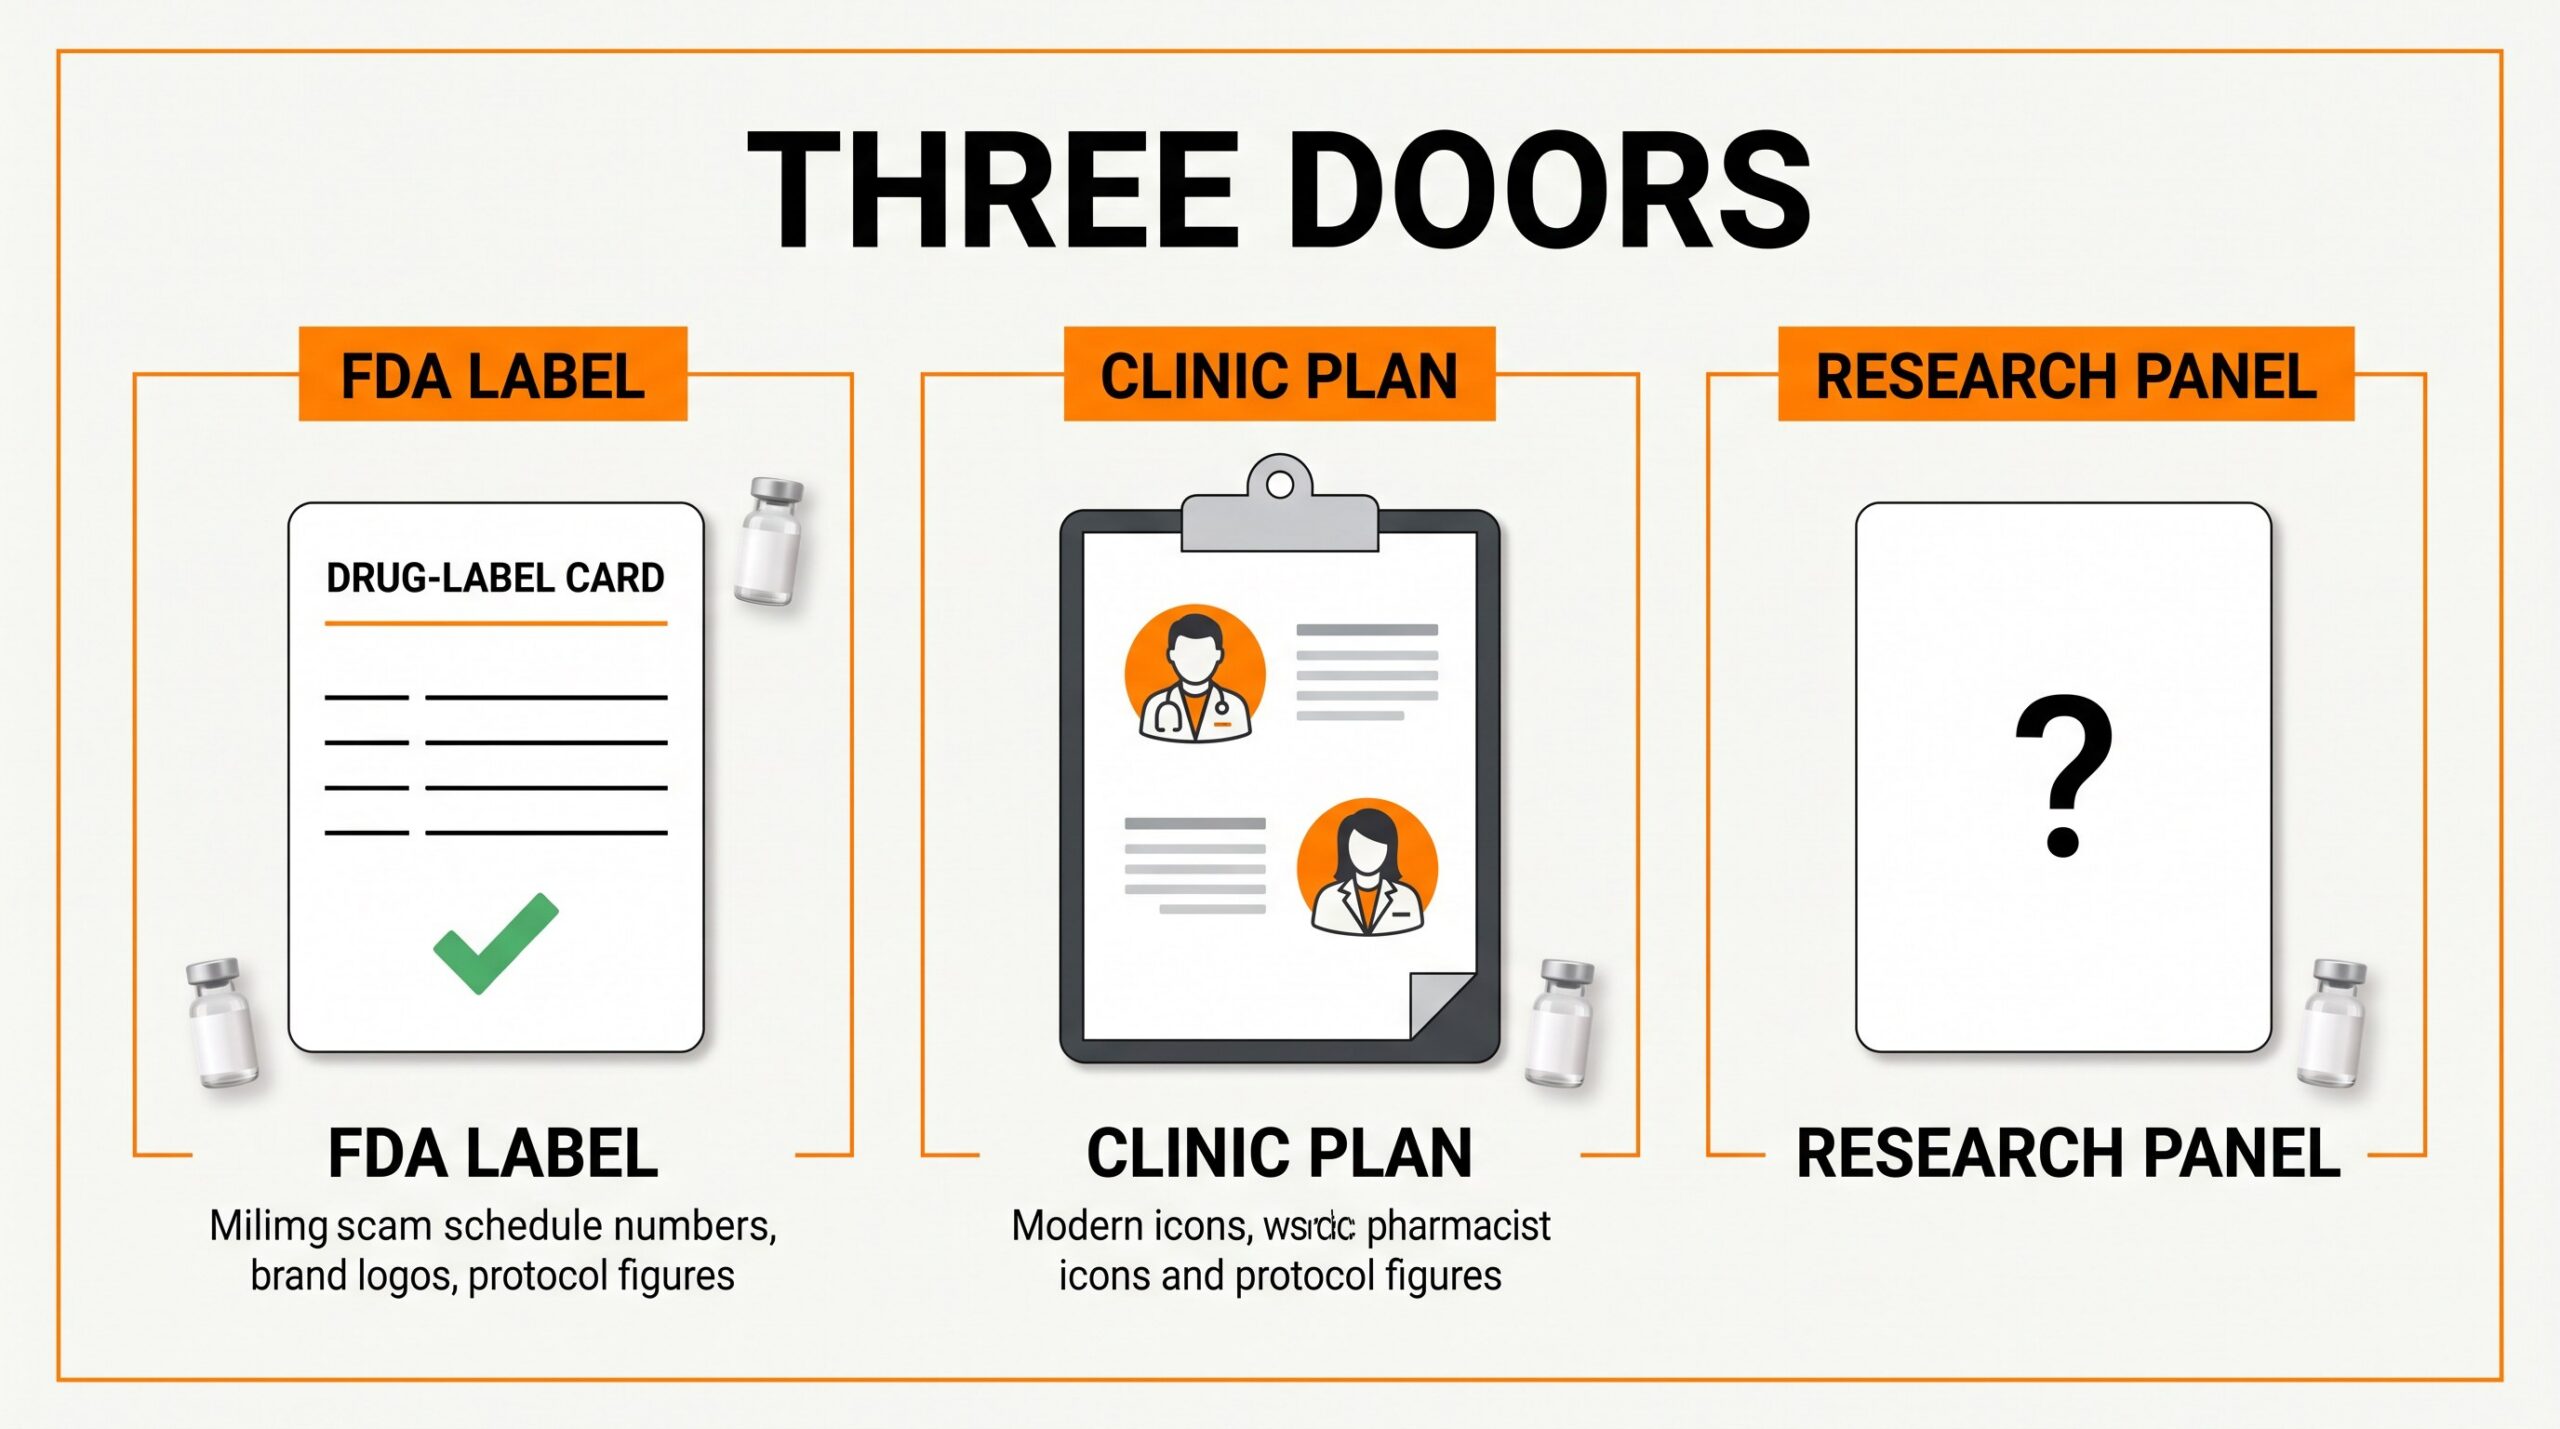
That question hides three different objects.
Object 1 is an FDA-approved peptide drug. Think semaglutide or tirzepatide. Those have labels, monitored plans, and huge trials. Dose talk sits in public files.
Object 2 is a compounded or clinic-ordered plan. A pharmacist and a clinician own that door. Rules still matter. Amount talk still belongs with them.
Object 3 is a research-shelf vial. Education and curiosity only on this free site. Thin human data for many names. A blank dose panel is not a free protocol for your body.
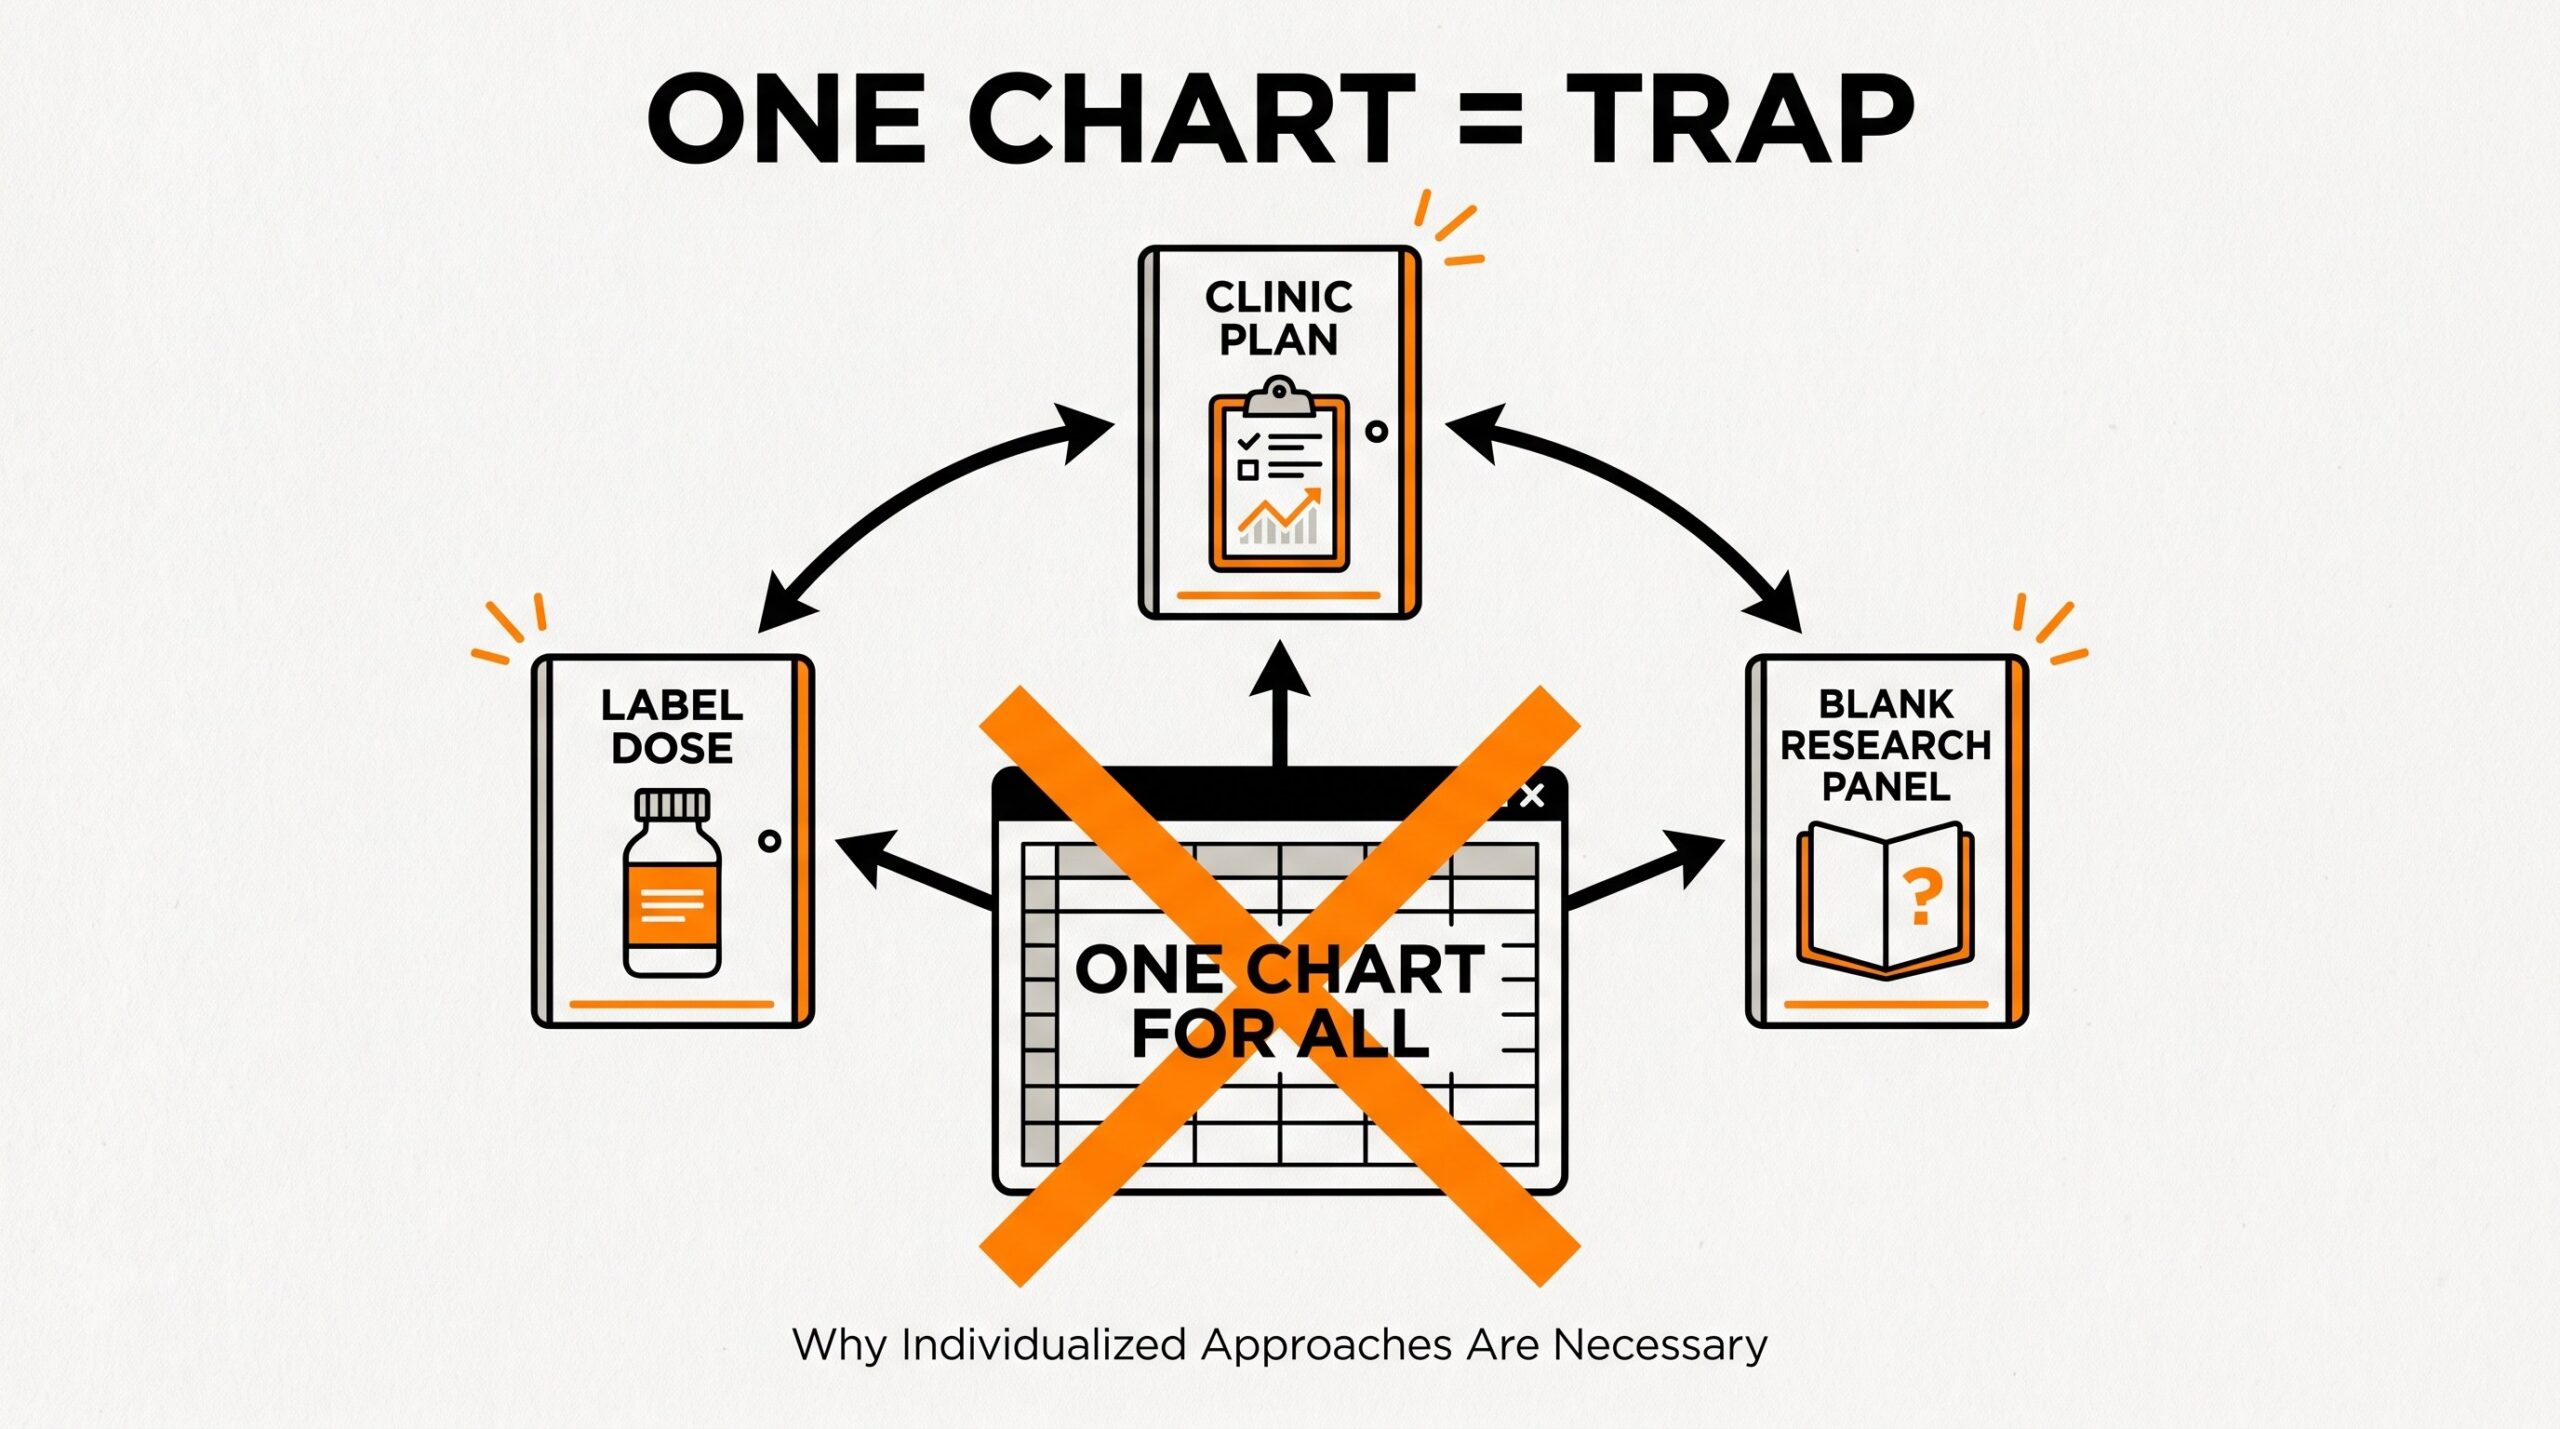
Why this matters: if you treat all three objects as one “peptide dosage,” the answer turns into a trap chart.
So what for you: name the object before you chase a number.
Three doors: FDA label vs clinic plan vs research blank panel
Here is the only picture I want stuck in your head.
An FDA-labeled peptide drug is like a car with a real odometer. Engineers ran the tests. Regulators published rules. The label still is not your personal plan. But the evidence lane is real.
A clinic or compounding plan is like a route a licensed driver owns. The map is not public forum lore. Pharmacists and clinicians still answer for sterility, law, and fit.
A research-shelf vial is more like a kit with no gauges. There may be animal papers. There may be a certificate of analysis. There may be a cool forum story. That is not the same as a labeled dose file for your body.
How sure are we? Pretty sure approved peptide drugs publish studied amounts in trials. Pretty sure many wellness names still live mostly in cells and animals. Pretty sure reconstitution math changes what people mean by “dose.” Not sure at all that a social clip equals a label.
Why this matters: if you cannot tell label from blank panel in one line, wait on the cart.
So what for you: ask which evidence lane a post is selling before you trust its dosage story.
Units literacy (mg, mcg, IU, U-100) without a protocol
People mix four unit languages online. That is how math mistakes start.
mg means milligram. One thousandth of a gram. Vial labels often use this.
mcg means microgram. One thousandth of a milligram. Tiny amounts. Easy to confuse with mg if you skip zeros.
IU means international unit. It is a biologic activity measure, not a simple weight copy-paste. Different peptides can use IU talk differently.
Units on a U-100 syringe are tick marks on a common insulin-style syringe. Those marks are not magic milligrams. They only make sense after concentration is known.
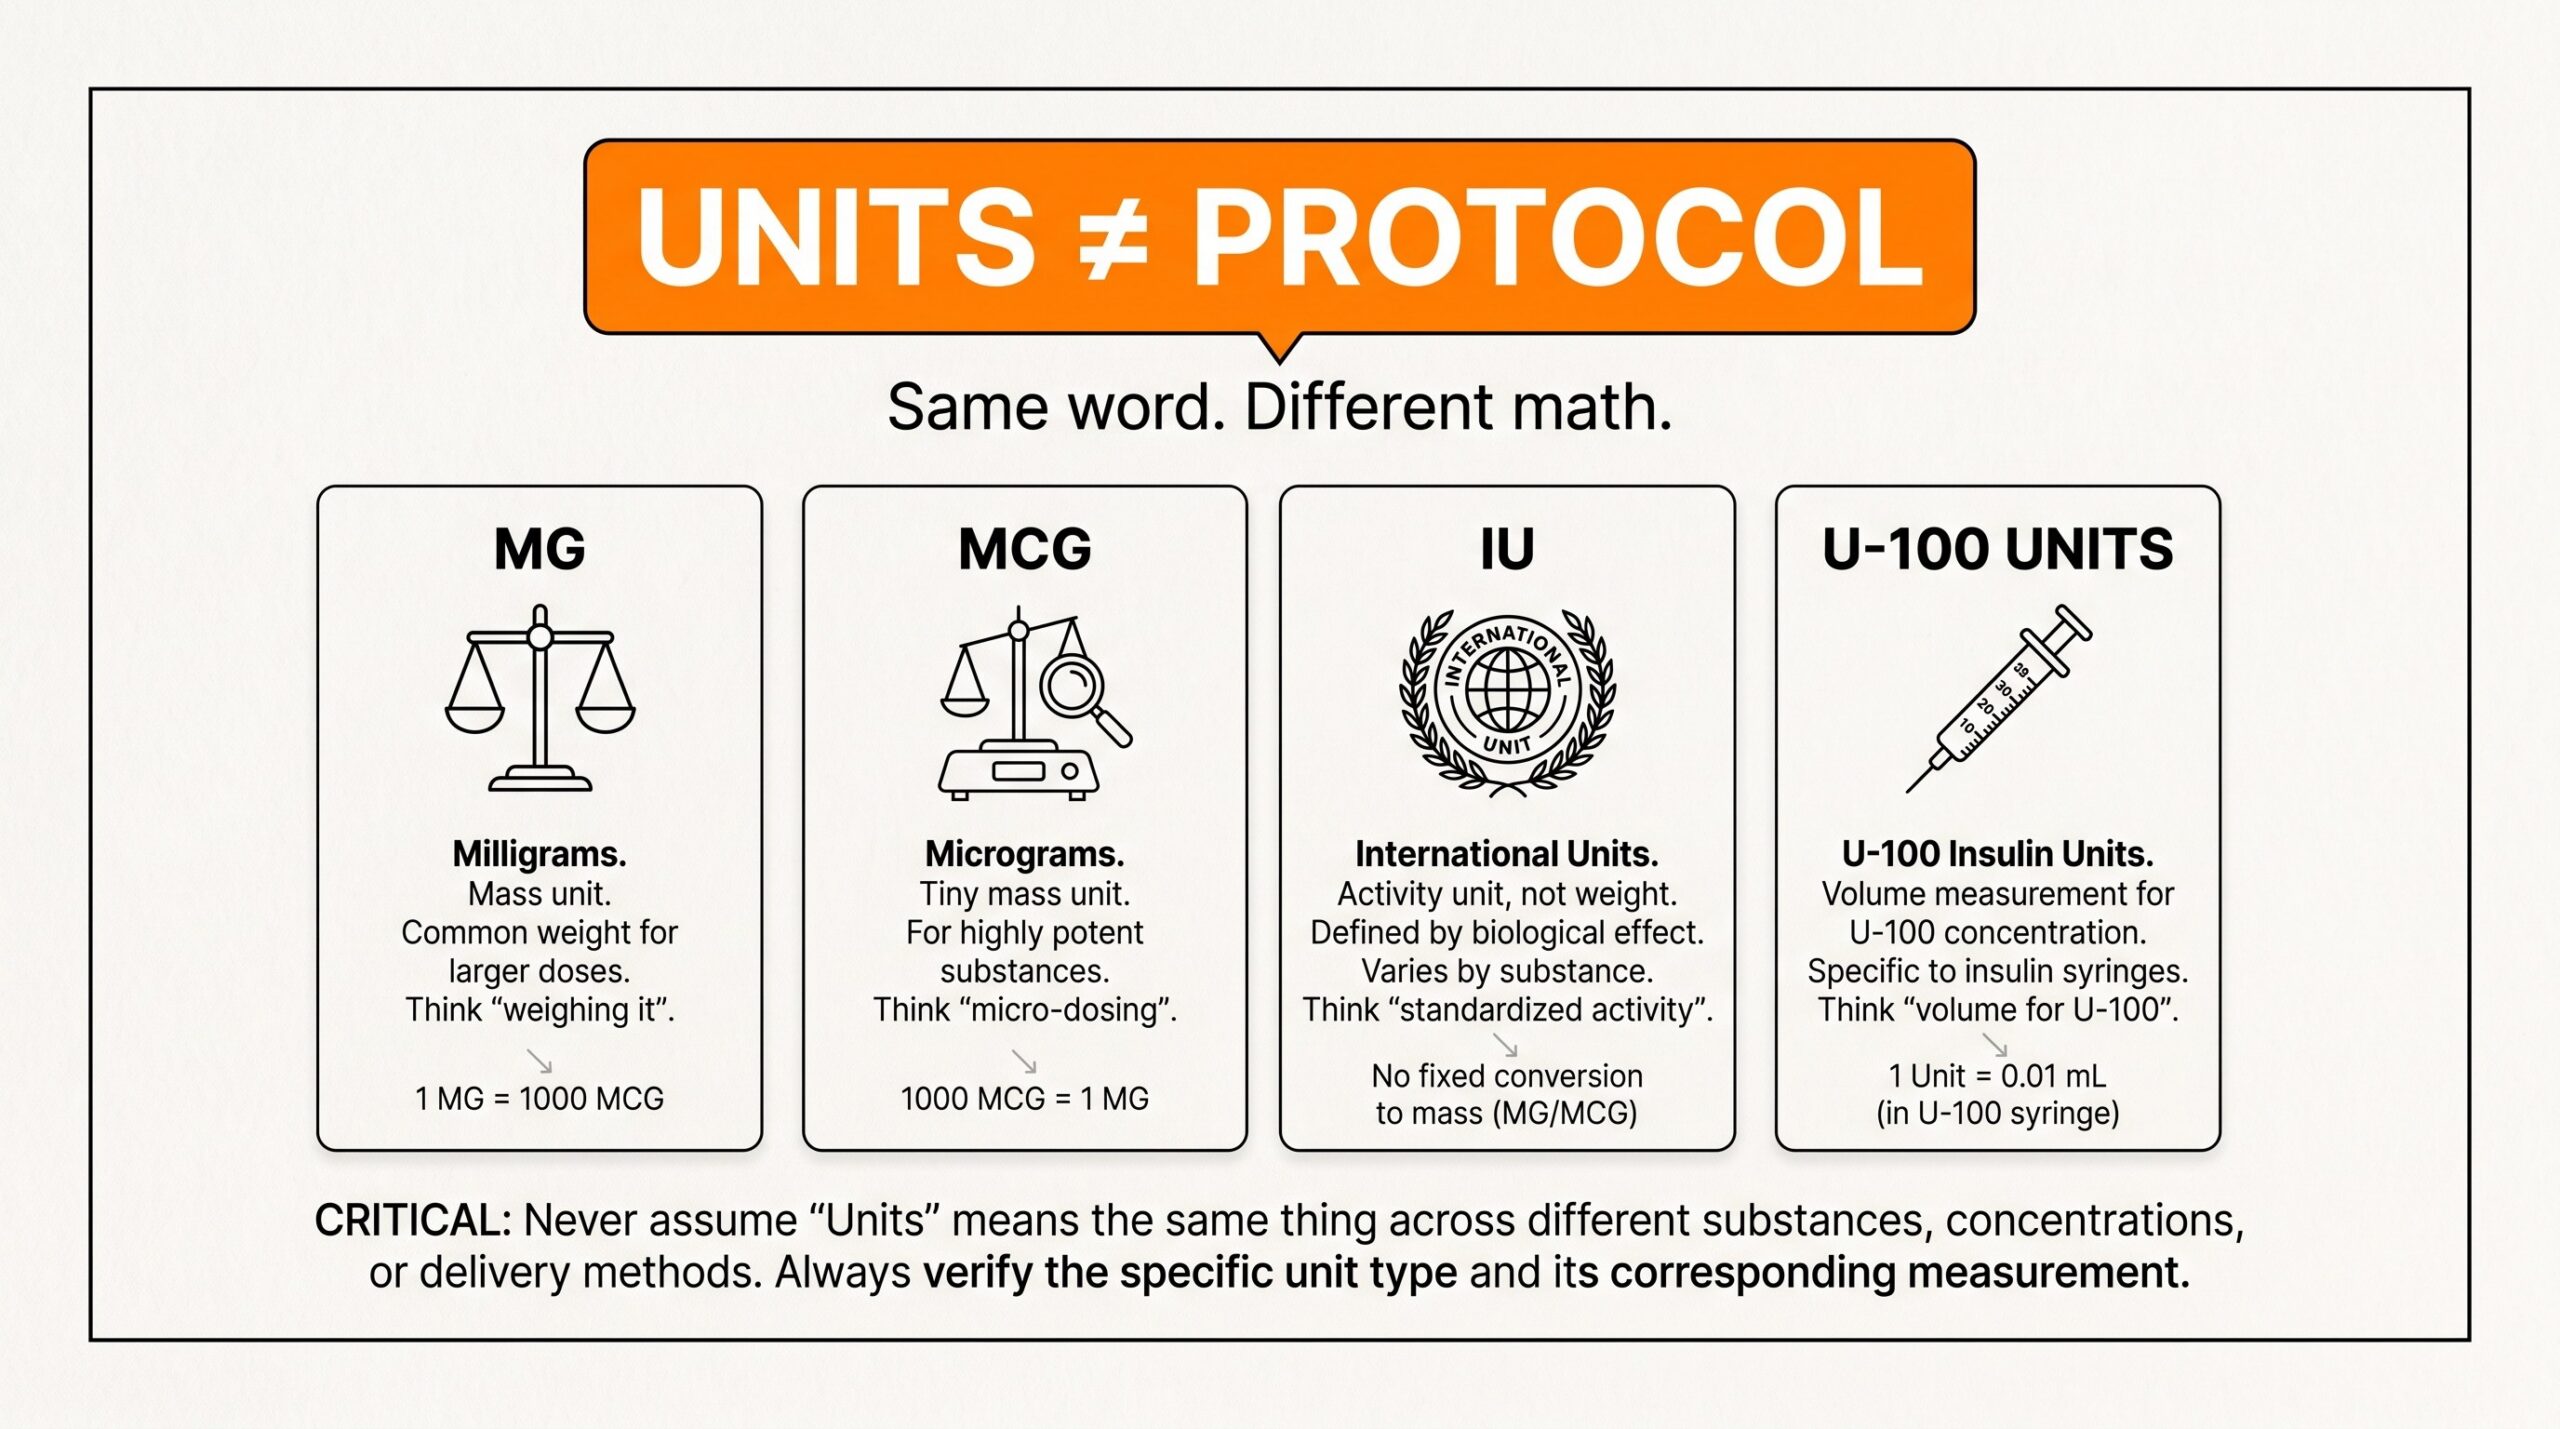
Insulin teaching is the cleanest public receipt for why unit talk matters. A 2014 safety review on insulin use flagged preventable dosing errors when pens, syringes, and concentration language get mixed. That is literacy, not a peptide stack tip.
Pen and syringe accuracy studies also exist in the insulin lane. They show why device design and force matter for measured amounts. They still do not become a free research-vial schedule here.
Why this matters: unit confusion can turn a careful reader into a wrong-number reader fast.
So what for you: learn the four unit words before you trust any chart that skips them.
Why reconstitution strength changes “dose” talk
Many research vials arrive freeze-dried. That means powder until liquid is added. The amount of liquid changes concentration. Concentration changes how many syringe ticks match a claimed amount.
So two people can say “same dose” and mean different syringe math if they added different volumes. That is why recon literacy matters. See how to reconstitute peptides, bacteriostatic water, and the peptide calculator.
A 2019 analysis looked at at-home freeze-dried medicine prep. Mixing took real work for patients and caregivers. That paper is about prep burden in chronic care. It is not a free research protocol. It still proves reconstitution is not a throwaway step.
Why this matters: without recon literacy, “peptide dosage” talk is half a sentence.
So what for you: finish the recon map before you argue about ticks on a syringe.
Evidence honesty — labeled drugs vs research blank panels
Labeled peptide drugs have studied amounts in big trials. Wilding and colleagues ran STEP 1. Once-weekly semaglutide. Adults with overweight or obesity. The trial used a published escalation path under a monitored plan. That is a dashboard with numbers. Not a blank panel.
Jastreboff and colleagues ran SURMOUNT-1. Once-weekly tirzepatide for obesity. Labeled peptide-drug dose maps sat inside a large randomized trial. Side effects and amounts both got tracked.
Lincoff and colleagues later reported SELECT. Semaglutide in people with obesity without diabetes. Huge labeled-drug evidence. Still not your personal free-site schedule.
Now flip the lane. McGuire and colleagues reviewed BPC-157 for musculoskeletal healing. They found a mountain of animal and cell work. Human work stayed tiny. Lee and Burgess later published a tiny intravenous safety pilot. Those papers matter. They still do not equal a Phase 3 labeled dose file.
Also hold the FDA compounding caution. The agency has publicly flagged that some bulk peptide substances used in compounding may present significant safety risks. Limited human data. Impurity questions. That is a regulator talking about uncertainty. It is not a free pass. It is not a scare meme either. It is a reason to keep lanes honest.
Why this matters: health pages get hurt if they blur “interesting research map” into “here is your public milligram chart.”
So what for you: be impressed by real trials. Do not confuse a blank forum spreadsheet with a label.
Keep / skip checklist
- Keep: asking which door a post is selling before you trust its dosage story.
- Keep: mg vs mcg vs IU vs U-100 literacy.
- Keep: recon and calculator pages before any research curiosity.
- Keep: clinic and pharmacist ownership for real ordered therapies.
- Skip: one universal peptide dosage chart for every name online.
- Skip: free-site milligram schedules for research vials.
- Skip: treating a research-shelf vial like an approved human medicine.
- Skip: ignoring a clinician because a clip felt confident.
Why this matters: keep/skip honesty saves money and cuts health-page risk.
So what for you: write your real dosage question in one sentence, then pick a door.
Three doors for next steps
Door 1 is basics first. What peptides are. Why dosage needs a comparison. Labels. Storage. Why a freeze-dried research vial is not a pen from a pharmacy. Start with what are peptides, are peptides safe, how to reconstitute peptides, bacteriostatic water, and peptide calculator.
Door 2 is clinic and pharmacist. Real ordered therapies. Monitored plans. Labeled peptide drugs with trial receipts. Clinicians own this door.
Door 3 is research curiosity map. How a class shows up in papers. Nearby research vials. COA literacy. Education only on this free site. Not a public stack chart. Not a public dosing table. Soft mastery lives in Pro.
Why this matters: people lose money when they buy Door 3 while the real problem was Door 1 or Door 2.
So what for you: match the door to the question before you click a code.
Partner research options (codes in the links)
Education first. You already have the dose map. Below are public options people park next to basics reading: reconstitution tools and common research vials from tracked partners. Codes fire in the links. Research-use and education framing only. Not a treatment claim. Not a claim these SKUs are your personal dosage chart.
Public basics + research maps
 Peptira
BAC Water
LEE Paramount
Recon Solution
LEE10 Peptira
Acetic Acid
LEE Peptira
BPC-157
LEE BioLongevity
BPC-157
LEE15 BioLongevity
TB-500
LEE15 Paramount
Wolverine Blend
LEE10Peptira BAC · LEE Paramount Recon · LEE10 Peptira Acetic · LEE Peptira BPC-157 · LEE BLL BPC-157 · LEE15 BLL TB-500 · LEE15 Paramount Wolverine · LEE10 Limitless home · LEE20
No Limitless VIP-login SKU is heroed here. Keep tracked homes handy too: Limitless LEE20, Paramount LEE10, Peptira LEE, S1 LEE10, and BioLongevity LEE15.
How to think about next steps
If you do not want to waste money on a universal dosage chart, start with Door 1 and the units story. Class clarity beats a forum spreadsheet every time. If you want the research map, learn Door 3 after the lanes click. Soft close to Pro for mastery frameworks. The free page’s job is still the map.
Why this matters: next steps that match the door save money. They also cut health-page risk.
So what for you: write your real dosage question in one sentence before you click a code.
Key takeaways (echo)
- Peptide dosage is a class map. Not a free therapy protocol.
- The best one-line picture is label dose vs clinic plan vs blank research panel. Same word. Different evidence lane.
- Labeled peptide drugs publish studied amounts in big trials. Research-shelf favorites often still lack that file. Reconstitution strength changes dose talk. Units literacy beats one chart. Basics and clinicians still beat hype clips. Start there.
Get the Peptide Playbook
Free email map for how to think about research peptides without the guru noise. No naked PDF dump — just the Playbook form.
Sources & Further Reading
- Wilding JPH, et al. Once-Weekly Semaglutide in Adults with Overweight or Obesity. N Engl J Med. 2021. PMID 33567185
- Jastreboff AM, et al. Tirzepatide Once Weekly for the Treatment of Obesity. N Engl J Med. 2022. PMID 35658024
- Lincoff AM, et al. Semaglutide and Cardiovascular Outcomes in Obesity without Diabetes. N Engl J Med. 2023. PMID 37952131
- Prescrire Editorial Staff. Insulin use: preventable errors. Prescrire Int. 2014. PMID 24516905
- Franzese C, et al. Burden of at-home preparation of lyophilized parenteral medications. Expert Opin Drug Deliv. 2019. PMID 30636541
- McGuire FP, et al. Regeneration or Risk? A Narrative Review of BPC-157 for Musculoskeletal Healing. Curr Rev Musculoskelet Med. 2025. PMID 40789979
- Lee E, Burgess K. Safety of Intravenous Infusion of BPC157 in Humans: A Pilot Study. Altern Ther Health Med. 2025. PMID 40131143
- U.S. Food and Drug Administration. Certain Bulk Drug Substances for Use in Compounding that May Present Significant Safety Risks. FDA compounding safety page
Educational research map only. Not medical advice. Not FDA-approved treatment claims. Partner links may earn a commission. Codes live in the links.